Because Nodules do not Follow Guidelines
The Problem
Whether or not to Biopsy - Being on the fence about next steps in the diagnostic journey can create anxiety and fear in you and your patient and potentially stalling next steps.
And for many pulmonary nodules you’re not even sure a biopsy is the right next step; the uncertainty in those cases can be just as challenging—stalling decisions and putting both you and your patient in a holding pattern.
-
Up to 13% of surgical lung resections from lung cancer screening programs are benign. (https://pmc.ncbi.nlm.nih.gov/articles/PMC10730375/)
-
Early detection improves survival rates significantly. (https://shorturl.at/CywEU)
The Solution:
LungLifeAI: Clinical Utility
More accurate assessment of pulmonary nodules.
Non-invasive blood-based test
Improves early lung cancer detection
Enhances clinical decision-making
Now included in the National Cancer Institute Early Detection Research Network as a CLIA-approved marker.

Utilizing the Power of AI
The LungLifeAI test uses a locked and validated machine learning-based image analysis algorithm to automatically identify Circulating Genetically Abnormal Cells (CGACs) from fluorescent imaging. To develop this classifier, this algorithm scanned thousands of cells, detecting abnormal chromosomal signal patterns, and applies predefined decision rules to classify CGACs with high precision. It minimizes human error and interobserver variability, making the test more reproducible and scalable for clinical use.
How LungLifeAI Works:
The Science Behind the Innovation
LungLifeAI is powered by AI and a FISH assay that identifies Circulating Genetically Abnormal Cells (CGACs) in a standard blood sample. These CGACs exhibit specific chromosomal abnormalities frequently found in lung cancer cells, allowing early detection of malignant transformation when imaging results are inconclusive.
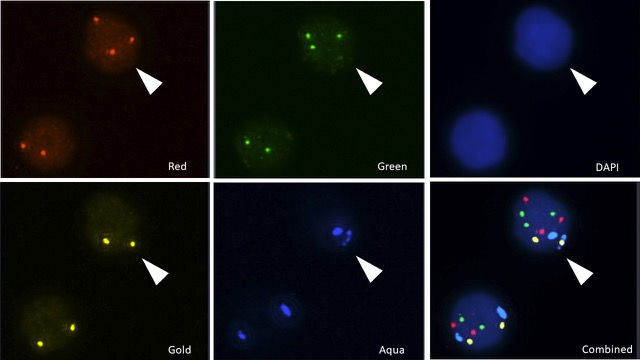
CGAC Identification
-
Illustrates the clear difference between normal and genetically abnormal cells under FISH imaging.
-
Normal cells show two signals per probe, while CGACs show multiple or missing signals, indicating genomic instability.
Key Benefits
SENSITIVITY & SPECIFICITY
-
Positive Predictive Value (PPV): 80%
-
Sensitivity: 83.8%
-
Specificity: 76.92%
-
Area Under the Curve (AUC): 0.78
-
Approximately 7 Day Turn Around Time
INDEPENDENCE FROM TRADITIONAL RISK FACTORS
LungLifeAI’s performance was not influenced by conventional clinical and radiological factors such as smoking history, previous cancer diagnosis, lesion size, or nodule appearance, suggesting it provides unique and valuable information beyond standard assessment criteria.
COMPARISON WITH EXISTING MODELS
Notably, the Mayo Clinic Model achieved an AUC of only 0.52 within the same study cohort. Highlighting LungLifeAI’s superior diagnostic accuracy in distinguishing benign and malignant nodules.
Implications for Clinical Practice
COMPLEMENTARY TO EXISTING DIAGNOSTIC TOOLS
LungLifeAI excels in small nodules where the uncertainty is greater and PET performs poorly, and serves as an adjunct to imaging studies, providing additional molecular insights allowing for more informed decision making for diagnosis and management.
EARLY DETECTION OF MALIGNANCY
Enhanced sensitivity facilitates the prompt identification of malignant nodules, enabling earlier intervention and potentially improving prognosis.
REDUCTION OF UNECESSARY INTERVENTIONS
By accurately identifying benign nodules with a Rule In test with high PPV, LungLifeAI may help avoid invasive procedures, reducing unwarranted patient risk and healthcare costs.
Clinical Validation of LungLifeAI
A pivotal study published in BMC Pulmonary Medicine evaluated the efficacy of LungLifeAI in predicting lung cancer among individuals with IPNs. The study enrolled 151 participants scheduled for biopsy across two renowned institutions: Mount Sinai Hospital and MD Anderson Cancer Center. The primary objective was to assess the correlation between LungLifeAI results and biopsy-confirmed diagnosis.
If you think it may be cancer, order a LungLifeAI test to minimize uncertainty & delays in diagnosis.
Clinical Highlights
CASE STUDY 1
-
Former Smoker (37.5 pack years)
-
No history of cancer
-
No underlying lung disease
-
Mayo Risk Score: 25%
November 2018
Initial Evaluation, CT scan shows solitary subsolid 1.3 cm nodule in upper left lobe
January 2020
Biopsy negative for lung cancer LungLifeAI test-increased risk
January 2021
Surgical resection of indeterminate nodule
Stage 1 Adenocarcinoma
Days LungLifeAI May Have Saved: 365
CASE STUDY 2
-
Former Smoker (78 pack years)
-
No history of cancer
-
No underlying lung disease
-
Mayo Risk Score: 47%
October 2019
Initial Nodule Size 1.68cm in left upper lobe
February 2020
Slight increase of nodule size
March 2020
Biopsy found atypical-rare cells
LungLifeAI test-increased risk
May 2020
Nodule negative for cancer (scar tissue)
Lymph Nodes N2 & N3 Small Cell Lung Cancer